.

General Discussion on any topic relating to CPAP and/or Sleep Apnea.
User avatar
NotMuffy
Posts: 962
Joined: Wed Sep 16, 2009 6:56 am
Location: Dunno. GPS is dead.

It's A Beautiful Day

Post by NotMuffy » Mon Jan 31, 2011 5:56 am

Where did you get that sleep hygiene list? You correctly question the Bright Light Therapy in the late afternoon thing. BLT should have a target:

http://www.sleepeducation.com/Treatment.aspx?id=4

but since this is "hygiene" and not "treatment", the cheapest and best BLT (or maybe BLH) is get outside first thing in the morning for 30 minutes. Even a cloudy day provides plenty of lux.

And don't be staring at the computer screen before bedtime. That'll burn up melatonin, too.

I think FL is now very important to the discussion (sorry I didn't see it sooner, but this ain't the pickup window at McSleepStudies).

I think you need to make sure that your upper airway is patent. RIgid obstruction will create fixed FL and be untreatable. Can you breathe through each nare freely? Then try putting lateral traction on the skin between the bridge of your nose and cheekbone. Does that make significant improvement (if so, maybe a Breathe-Right Strip may help).

I'd ask your physician what their approach to treating FL is, and then ask, "Upon opening the Collection File, it appeared that due to filter settings, the tech was viewing

Image

when they should have been viewing

Image

What's up with that?"
"Don't Blame Me...You Took the Red Pill..."

User avatar
NotMuffy
Posts: 962
Joined: Wed Sep 16, 2009 6:56 am
Location: Dunno. GPS is dead.

Re: It's A Beautiful Day

Post by NotMuffy » Mon Jan 31, 2011 6:17 am

BTW, immediately after the above epoch, intervention to 10cmH2O gave improvement to the FL waveform:

Image

Yet, this was temporary, and shortly thereafter the process repeated at 12 cmH2O.

A bilevel approach (a flow burst as opposed to an overall pressure increase) may provide a better and more stable solution.
"Don't Blame Me...You Took the Red Pill..."

User avatar
secret agent girl
Posts: 574
Joined: Tue Nov 10, 2009 2:15 pm

.

Post by secret agent girl » Mon Jan 31, 2011 7:39 am

.
Last edited by secret agent girl on Sun Feb 06, 2011 10:09 pm, edited 1 time in total.

User avatar
secret agent girl
Posts: 574
Joined: Tue Nov 10, 2009 2:15 pm

.

Post by secret agent girl » Mon Jan 31, 2011 8:05 am

.
Last edited by secret agent girl on Sun Feb 06, 2011 10:09 pm, edited 1 time in total.

-SWS
Posts: 5285
Joined: Tue Jan 11, 2005 7:06 pm

Re: pap treatment, take 2

Post by -SWS » Mon Jan 31, 2011 8:23 am

secret agent girl wrote: What would be really helpful to me at this point would be:
**More of you lurkers to jump in, even if “just” with encouragement
Good luck, secret agent girl! A few comments before I retreat into my own TN based physical pain today:

1) Flow Limitations: NotMuffy discovered that graph filters in your past NPSG masked your flow limitations. I'm under the impression that some clinics still ignore flow limitations and focus on apneas and hypopneas. I'd call your clinic before the upcoming NPSG and ask about their flow limitation DX and TX policy. If they ignore FL or play down the importance of FL, then I'd cancel the sleep study and find a clinic that focuses on FL based SDB as much as apnea and hypopnea based SDB

2) Pain: Where is your physical pain now compared to when you had the NPSG that NotMuffy is currently analyzing? There's a chance that pain-related alpha intrusions are now one of your sleep spoilers. I'd ask the sleep clinic to look for alpha intrusions as well---since that may be one of your sleep issues now versus before.

3) Sleep Aids During the NPSG: This is a tough call IMHO. The inherent dilemma in your case is that if you can't sleep during the NPSG, then your disordered sleep obviously cannot be measured. If there was easy advice about HOW to sleep well during an NPSG, then that same advice could be applied nightly at home as well. And you wouldn't need the sleep study.

If you think there's a GOOD chance you can sleep naturally during the NPSG, then pharmaceutical sleep aids won't risk masking/skewing the underlying central breathing, wake/arousal, and perhaps even alpha-intrusion characteristics you endeavor to measure. Conversely, if you know there's a poor chance of sleeping during the NPSG without a sleep aid, then IMHO you're better off taking the sleep aid. You won't perfectly recreate your home-based sleep problems that way, but there will hopefully be characteristic sleep problems for them to study----there usually are. Sleep deprivation is one alternative to a sleeping pill. I intentionally reported in to my second of two sleep studies very sleep deprived. That way I was able to sleep during my second NPSG. I still presented more than my share of spontaneous arousals considering how sleep deprived I was. But at least I slept.


Call for lurkers and other semi-lurkers to offer secret agent girl practical advice or just wish her luck! Again, good luck. SAgirl! And thanks again for doing this, NotMuffy!

User avatar
Madalot
Posts: 4287
Joined: Sat Jan 30, 2010 7:47 am

Re: pap treatment, take 2

Post by Madalot » Mon Jan 31, 2011 9:05 am

I'll pipe in here and offer some encouragement. I know it's frustrating, but I think you're getting exceptional input here and eventually, you all will get this all figured out.

Keep on plugging, keep on asking questions. The experts here are very, very good.

_________________
Mask: FlexiFit HC431 Full Face CPAP Mask with Headgear
Humidifier: HC150 Heated Humidifier With Hose, 2 Chambers and Stand
Additional Comments: Trilogy EVO. S/T AVAPS, IPAP 18-23, EPAP 10, BPM 7

User avatar
SleepingUgly
Posts: 4690
Joined: Sat Nov 28, 2009 9:32 pm

Re: pap treatment, take 2

Post by SleepingUgly » Mon Jan 31, 2011 9:14 am

Secret Agent Girl, I'm rooting for you!
Never put your fate entirely in the hands of someone who cares less about it than you do. --Sleeping Ugly

User avatar
NotMuffy
Posts: 962
Joined: Wed Sep 16, 2009 6:56 am
Location: Dunno. GPS is dead.

Re: It's A Beautiful Day

Post by NotMuffy » Wed Feb 02, 2011 5:49 am

secret agent girl wrote:PS: It is a Beautiful Day--or were you just reminding me of one of my favorite bands from the sixties?
http://www.itsaboutmusic.com/beautifulday.html
Well, the self-entitled First Album was great, but actually my Mind Collage is going Warm Sun > Gorgeous Blue Sky (at the time of the original post, anyway) > U2 > Bono > Edge > IABD > LaFlamme.

Since we're talking about flow waves, bilevel, therapy tolerance, and filter settings, now is a great time to go back (if everyone hasn't done that already) and review one of the "Best of" threads, "BiLevel Therapy P****s" (sorry, that word is out of context).

Anyway, we're in the middle here:

Titrating To What?

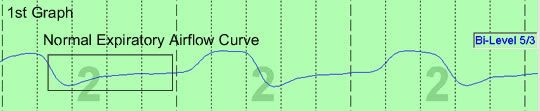
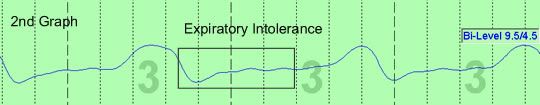
Basically, one poster is saying that there should be zero tolerance for flow limitations, and a key component of that is a phenomenon termed "Expiratory Intolerance", while another poster is saying that there's NSFT called "Expiratory Intolerance", and it's simply (1) a misinterpretation of the waveform, and (2) even if there were such a thing, the treatment choice (lowering EPAP) would be totally inappropriate.

The Proposed "Normal" Waveform:

Image

The Proposed "Abnormal" Waveform:

Image

Now interestingly, you have this same "expiratory intolerance" waveform (enhanced through adjustment (removal) of filters):

Image

Here are the proposed "Bumps of Expiratory Intolerance (BEI)":

Image

However, superimposing the EKG waveform:

Image

we can now clearly see that the "bumps" are simply artifact created by the pounding of the heartbeat that is picked up in the flow channel. Titrating to that would make no sense.
"Don't Blame Me...You Took the Red Pill..."

User avatar
NotMuffy
Posts: 962
Joined: Wed Sep 16, 2009 6:56 am
Location: Dunno. GPS is dead.

Chucksicle

Post by NotMuffy » Wed Feb 02, 2011 6:17 am

BTW, the Groundhog is frozen hard as a rock.

I think that's a bad sign.
"Don't Blame Me...You Took the Red Pill..."

User avatar
NotMuffy
Posts: 962
Joined: Wed Sep 16, 2009 6:56 am
Location: Dunno. GPS is dead.

I Like Puzzles Anyway

Post by NotMuffy » Wed Feb 02, 2011 6:30 am

In the Good News, Bad News Category:

I found the morning newspaper.

Unfortunately, I found it with the snow blower.

Looks like it's gonna be one of those days.
"Don't Blame Me...You Took the Red Pill..."

User avatar
KatieW
Posts: 1671
Joined: Sun Sep 27, 2009 11:07 am
Location: southern AZ

Re: pap treatment, take 2

Post by KatieW » Wed Feb 02, 2011 8:51 am

Secret Agent Girl, I'm one of the lurkers on this thread. I have nothing to add to this thread, but thank you for sharing this with us, so we can learn, and cheer for you.

_________________
Mask: Pico Nasal CPAP Mask with Headgear
Additional Comments: Resmed AirCurve 10 ASV and Humidifier, Oscar for Mac
KatieW

User avatar
NotMuffy
Posts: 962
Joined: Wed Sep 16, 2009 6:56 am
Location: Dunno. GPS is dead.

Bombay Calling

Post by NotMuffy » Fri Feb 04, 2011 4:55 am

OK, given your other thread re: weight loss, I'm kinda gettin' the feeling you're taking a slightly different direction in treatment approach, and maybe deferring PSG for a bit might not be a bad idea.

I mean, if you end up with a 30% weight loss, trying to microanalyze these FLs might be a little like Yossarian with the band-aid on the airplane.

In what may be a couple final thoughts, an interesting study showing the

Relationship Between Functional Residual Capacity And Obstructive Sleep Apnea
This study confirms prior observations that a low FRC is a risk factor for developing sleep disordered breathing.
but that
lack of association between FRC and AHI during REM sleep indicates that factors other than lung volume
which is kinda telling me that this phenomenon is a little CompSAS-y in nature (because it alters plant gain), and isn't strictly due to reducing tracheal traction (a la Split_City research).

Since weight loss will probably increase FRC, pre- and post-weight loss PFTs would lend discussion fodder.
secret agent girl wrote:The sleep doctor is not sleep medicine board certified, though she works in a practice with with some partners who are. It's actually one of these partners that dictated the report at the beginning of my 1st study. Would I be better of seeing a doctor who is certified?
Your most recent sleep log upload shows some good sleep hygiene stuff, but those awakenings look pretty significant:

Image

If you choose to see another physician, try to get one who is not only Board-Certified, but is sharp in sleep itself. A clue would be to see if they are sub-certified in CBT.
"Don't Blame Me...You Took the Red Pill..."

User avatar
NotMuffy
Posts: 962
Joined: Wed Sep 16, 2009 6:56 am
Location: Dunno. GPS is dead.

Bulgaria!

Post by NotMuffy » Fri Feb 04, 2011 5:53 am

Although your sleep study was a split and you've got a lot of wake in the titration portion such that there's not a great deal of data to analyze, this is an area that I believe may offer some good insights:

Image

This is at about 0500 on 12 cmH2O PAP while on your left side (and usually OSA is less severe in lateral sleep than supine because of the way the airway collapses, so overall information is incomplete).

OSA severity can also change within NREM. "Light" NREM (stages 1 and 2) is more susceptible to OSA than "deep" NREM (stage 3)-- or, put another way, if you can get to NREM 3, breathing becomes stable regardless of virtually everything else.

This may offer credibility to the CompSAS argument. While breathing stability appears in NREM3 (expected), it is maintained in REM ("Sparkly")(although this is on 12cmH2O and a relative ton of pressure, but one would think that if you're FL-y on 12 in light NREM, you would have been FL-y on 12 in REM).

Gotta run. cya.
"Don't Blame Me...You Took the Red Pill..."

User avatar
robysue
Posts: 7520
Joined: Sat Sep 18, 2010 2:30 pm
Location: Buffalo, NY
Contact:

Re: Bulgaria!

Post by robysue » Fri Feb 04, 2011 7:18 am

NotMuffy wrote: OSA severity can also change within NREM. "Light" NREM (stages 1 and 2) is more susceptible to OSA than "deep" NREM (stage 3)-- or, put another way, if you can get to NREM 3, breathing becomes stable regardless of virtually everything else.
[/quote]
NotMuffy,

This caught my eye for several reasons. Can you explain a bit more about deep NREM (stage 3) vs. light NREM?

Also can you explain the difference between stable and unstable NREM? How do they tell during the sleep test when NREM is unstable?

_________________
Machine: DreamStation BiPAP® Auto Machine
Mask: Swift™ FX Nasal Pillow CPAP Mask with Headgear
Additional Comments: PR System DreamStation and Humidifier. Max IPAP = 9, Min EPAP=4, Rise time setting = 3, minPS = 3, maxPS=5

User avatar
secret agent girl
Posts: 574
Joined: Tue Nov 10, 2009 2:15 pm

.

Post by secret agent girl » Fri Feb 04, 2011 7:23 am

.
Last edited by secret agent girl on Sun Feb 06, 2011 10:07 pm, edited 1 time in total.